
Fertility and conception: what the evidence says
Trying for a baby shouldn’t turn sex into a chore. Here is what health bodies say about the fertile window, how often to have sex, the myths about positions, how long it usually takes and when to seek help. And how to look after desire along the way.
The fertile window: the six days that count
Pregnancy is only possible on a few days of each cycle. The American Society for Reproductive Medicine (ASRM) defines the fertile window as the six-day interval ending on the day of ovulation. Sperm can wait several days for the egg to be released; the egg, by contrast, survives for much less time. For a refresher on how the process works, see the definition of human reproduction.
Within that window, sex in the two days before ovulation has the best chance of success; on the day of ovulation itself the odds already fall.
- Cervical mucus: when it becomes more abundant, clear and stretchy, ovulation is close. In the studies reviewed by ASRM, pregnancy rates were around 38% on the day of peak mucus, compared with 15–20% the day before or after.
- Ovulation tests: they detect the rise in LH hormone in urine; ovulation usually follows within two days. They give false positives in around 7% of cycles.
- Calendar apps: according to ASRM, they predicted the day of ovulation correctly in at most 21% of cases. Use them as a rough guide, not a clock.
How often: every 1–2 days or 2–3 times a week
The two most widely cited references say almost the same thing, from different angles:
| Organisation | Recommendation | Best suited to |
|---|---|---|
| ASRM (United States) | Every 1–2 days during the fertile window | People tracking their fertile days |
| NICE (United Kingdom) | Every 2–3 days throughout the cycle | People who would rather not pinpoint ovulation |
Having sex more often does no harm. ASRM advises not limiting frequency: more than five days of abstinence can lower sperm counts, while intervals as short as two days are linked to normal sperm concentration. “Saving it up” for the key day achieves nothing.
The NICE approach has a practical advantage: it covers the fertile window without needing to know when ovulation happens, which takes a lot of pressure off.
Positions, legs in the air and lubricants: myths and facts
This is one of the most persistent myths, so let’s be clear: there is no evidence that any sex position increases the chance of pregnancy. ASRM states this in its committee opinion on natural fertility: coital position does not affect fecundability, that is, the chance of pregnancy in each cycle.
The same goes for lying with your legs in the air or your pelvis raised after sex. The belief that it helps sperm on their way “has no scientific foundation”, according to ASRM. Even in assisted reproduction, NICE notes that more than 20 minutes of bed rest after embryo transfer does not improve outcomes.
That is why the positions in this guide are suggested for comfort, enjoyment and taking the pressure off, never to “boost” fertility.
Lubricants and spermicides: this is where a change does help. In the laboratory, many water-based lubricants reduce sperm motility by 60% to 100%, and olive oil or saliva can also affect it. According to ASRM, lubricants based on hydroxyethylcellulose, mineral oil and canola oil showed no such effect. Spermicides are designed precisely to disable sperm: they are a contraceptive method. If you need lubricant, read how to choose a lubricant and look for one labelled as suitable when trying to conceive.
How long it takes and when to seek help
Taking a few months is normal. According to NICE, more than 80% of couples in which the woman is under 40 and who have regular sex without contraception conceive within one year. Of those who don’t, about half do so in the second year: more than 90% within two years. ACOG estimates that for healthy couples in their twenties or early thirties, the chance of pregnancy in any single cycle is 25–30%, falling to less than 10% by age 40.
Infertility is common. The WHO estimates that around 17.5% of the adult population, roughly 1 in 6 people, experience it; it defines infertility as failing to achieve a pregnancy after 12 months or more of regular unprotected sex.
When to seek help:
- After 12 months of regular sex without contraception and no pregnancy.
- After 6 months if the person trying to conceive is 35 or older, according to ASRM and ACOG. In the UK, NICE advises earlier referral from age 36.
- Straight away from age 40, according to ACOG.
- Sooner if there is a known cause of infertility or a history of factors that predispose to it, a health condition or regular medication (NICE, NHS).
- Assessment involves both partners: NICE recommends that both are assessed.
If you are trying to conceive with donor sperm or through insemination, the timescales and tests are different: it is best to talk to a fertility service from the start.
Lifestyle: what does make a difference
- Folic acid: NICE recommends 0.4 mg (400 micrograms) a day from before conception until week 12 of pregnancy, as it reduces the risk of neural tube defects. Some people need a higher dose of 5 mg on medical advice.
- Smoking: smoking reduces the fertility of the person trying to conceive, according to NICE, and ASRM describes it as having substantial adverse effects. In the partner providing sperm it is linked to poorer semen quality.
- Alcohol: the NHS advises avoiding alcohol while trying to conceive. NICE sets a maximum of 1–2 units once or twice a week, avoiding getting drunk; in the partner providing sperm, drinking to excess harms semen quality.
- Weight: with a body mass index (BMI) of 30 or over, conceiving is likely to take longer, according to NICE.
- Coffee: 1–2 cups a day do not appear to affect fertility or pregnancy, according to ASRM.
Once you are pregnant, the pregnancy and postpartum guide explains what changes in your sex life during pregnancy and after the birth.
The stress of “sex on a schedule” and how to manage it
Trying for a baby can take its toll on desire. ASRM notes that the stress of trying to conceive can reduce sexual self-esteem, satisfaction and how often people have sex, and that the effect is greater when sex is tied to an ovulation test or a strict schedule. NICE adds that stress can affect the relationship and lower libido.
- Go for the broad approach: every 2–3 days throughout the cycle covers the fertile window without watching the calendar.
- Keep sex “for a reason” separate from sex “just because”: make time for encounters with no goal, including ones without penetration, so pleasure doesn’t drop off the agenda.
- Remember responsive desire: many people don’t feel like it before starting, but once they start. Understanding this eases guilt; we explain it in spontaneous and responsive desire.
- Talk about mismatches: if one person experiences it as an obligation and the other as urgent, the gap grows. You’ll find tips in desire discrepancy in couples.
- If pain, erection difficulties or paralysing anxiety appear, mention it to a health professional: it can usually be treated, and it also affects your chances.
Comfortable positions to enjoy without pressure
No position increases the chance of pregnancy. These are chosen for comfort, closeness and low effort, so that sex stays an encounter rather than a task. Keep the ones you want to come back to.
Comfortable and low-effort for any day
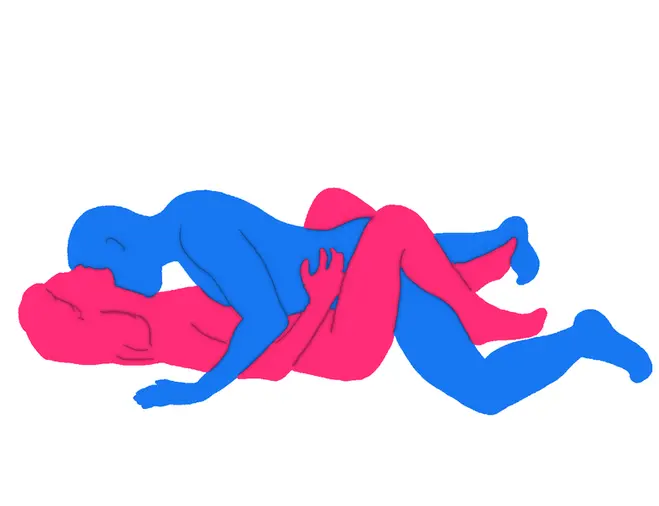
The MissionaryBajo
Face to face and low effort for the receiving partner. A pillow under the head is enough to be comfortable; there’s no need to raise the pelvis.

The SpoonBajo
Side by side and cuddled up, with gentle movements. One of the most relaxed options for tired days or when you fancy something calm.
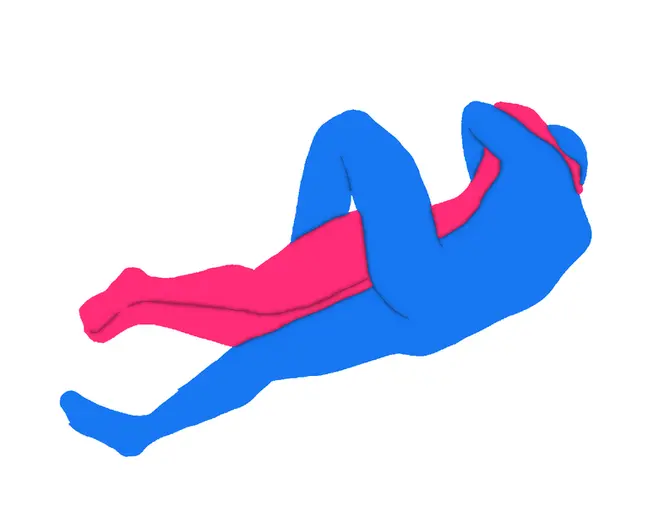
The Half Moon EncounterBajo
On your sides, face to face: you can look at each other, kiss and talk without anyone bearing the other’s weight.
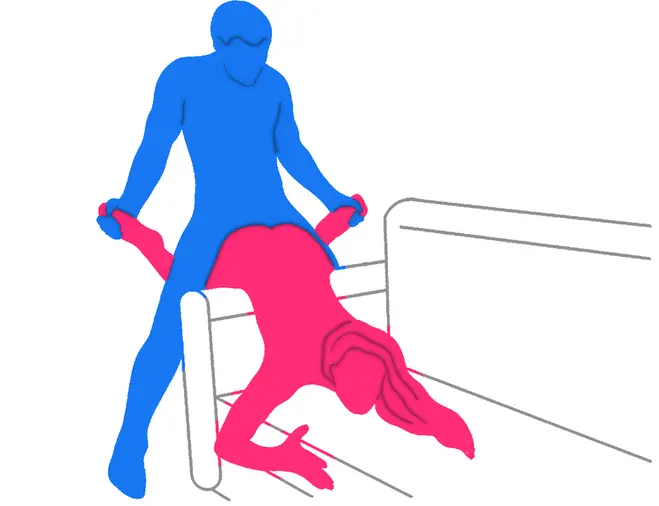
The Cobra (Embracing Hug)Bajo
Face to face, wrapped in an embrace: it puts skin-to-skin contact ahead of rhythm.
The receiving partner sets the pace
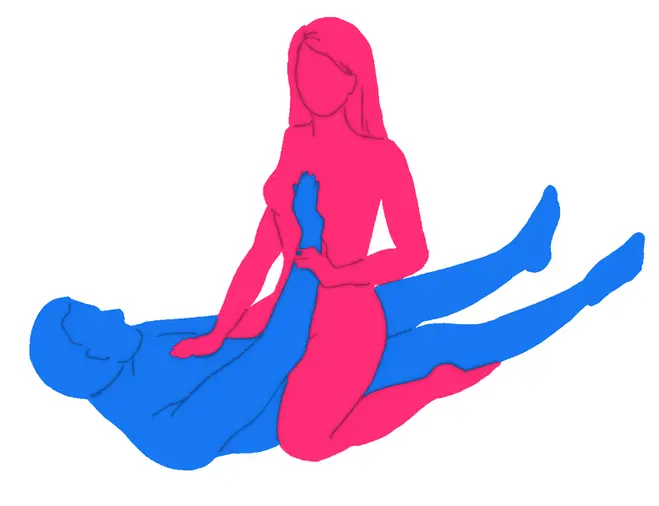
The CowgirlMedio
The receiving partner is on top and decides the rhythm, depth and pauses. Helpful when scheduled sex feels tense and you want to be in control.
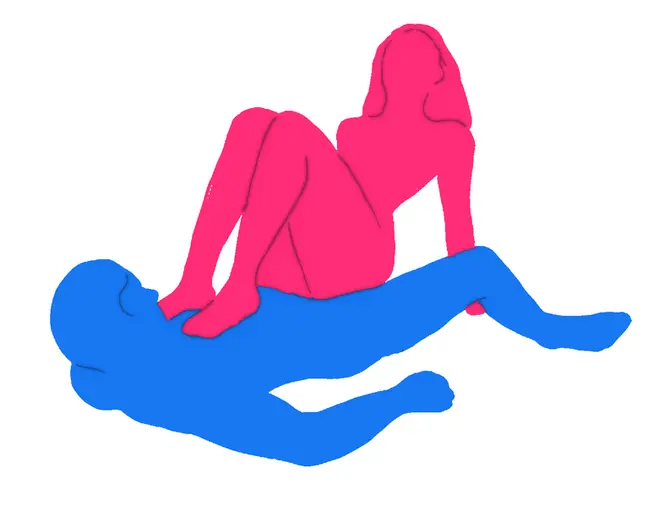
The PathMedio
On top and face to face: the partner above controls the movement and the other has their hands free to caress.
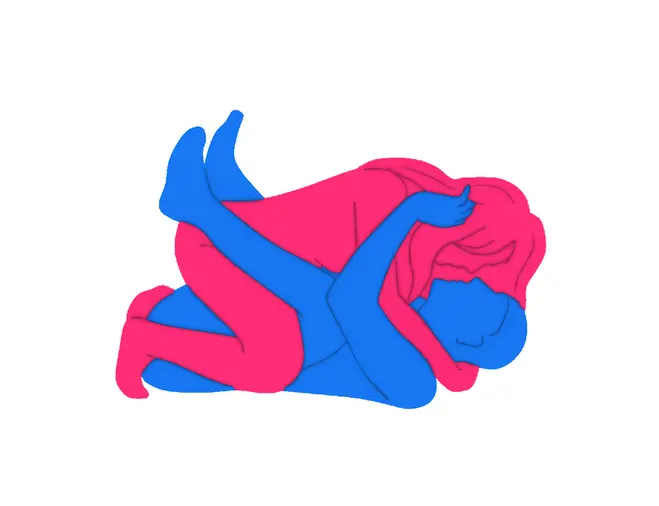
The Fifth ElementMedio
On top and chest to chest: short movements and maximum contact, for a slow, close encounter.
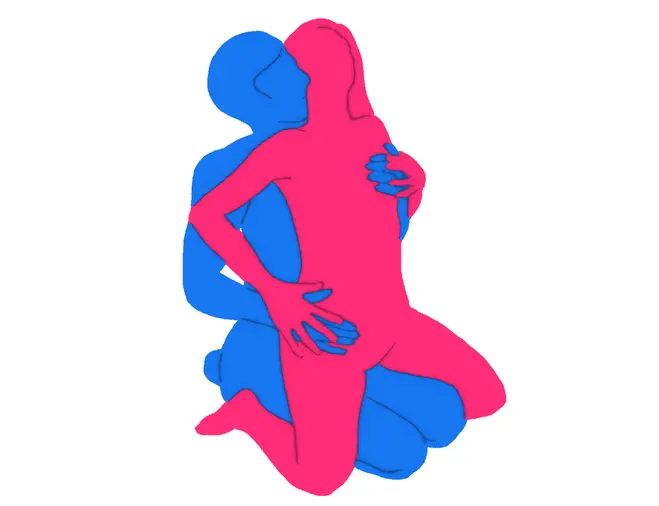
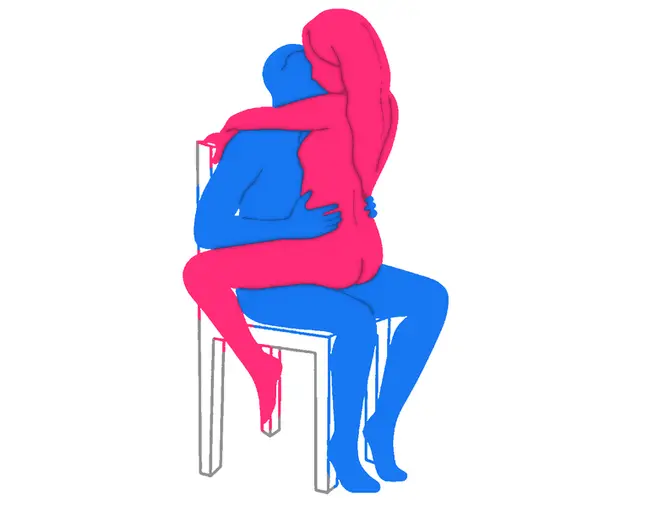
On a Chair (Straddling)Bajo
Straddling on a chair with feet on the floor: a change of scene that breaks the routine without demanding effort.
To ease the pressure and bring back pleasure
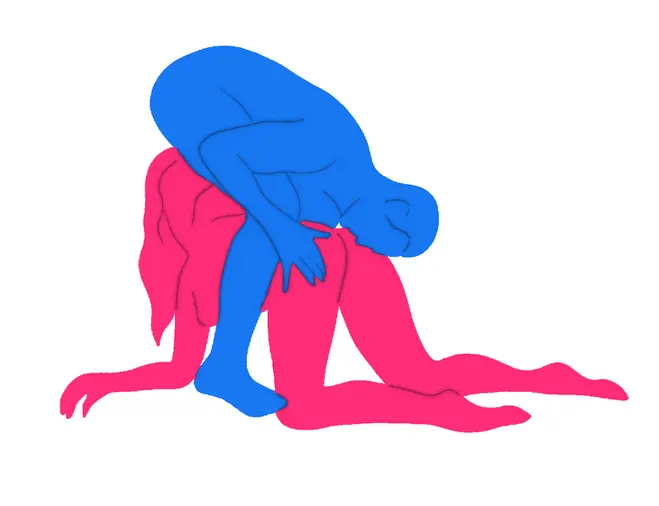
Foreplay (Preliminaries)Bajo
Taking time over foreplay helps arousal build, especially when desire is responsive and doesn’t show up before you start.
Tantric Sex (Slow Sex)Bajo
A slow pace and shared breathing: the focus is on feeling, not the goal, which matters when the calendar weighs heavy.

Erotic MassageBajo
An encounter without penetration for days outside the fertile window: it keeps intimacy going without everything revolving around pregnancy.
Best left aside
While you are trying to conceive, it’s best to let go of these ideas and habits, because they don’t help or may even work against you:
- looking for “the position that gets you pregnant”: it doesn’t exist;
- lying with your legs in the air or your pelvis raised after sex: it doesn’t increase the chances;
- going several days without ejaculating to “save up” sperm: more than five days of abstinence can lower the count;
- using lubricants that aren’t fertility-friendly, olive oil, saliva or spermicides;
- relying only on a calendar app to know your ovulation day;
- forcing demanding positions or carrying on through pain: if it hurts, stop and seek advice.
Keep reading
Articles
Definitions and contraception
Position lists
Frequently asked questions
Is there a sex position that helps you get pregnant?
No. The American Society for Reproductive Medicine (ASRM) concludes there is no evidence that position affects the chance of pregnancy. Choose whichever feels most comfortable and enjoyable.
Does putting your legs up after sex help?
It has no scientific basis. Lying down afterwards doesn’t increase the chance of pregnancy, so you can get up and carry on as normal.
How often should you have sex to get pregnant?
Every 1–2 days during the fertile window or, without tracking anything, every 2–3 days throughout the cycle. Having sex more often does no harm.
Which are the fertile days?
The six days ending on the day of ovulation. The chances are highest with sex in the two days before ovulation.
How long does it normally take to get pregnant?
According to NICE, more than 80% of couples conceive within a year and more than 90% within two. Taking several months is normal.
When should you see a doctor if you’re not getting pregnant?
After 12 months of trying; after 6 if the person trying to conceive is 35 or older, and sooner if they are 40 or over or there is a known cause. Ideally both partners should be seen.
Sources
- NICE. Fertility problems: assessment and treatment (CG156). National Institute for Health and Care Excellence. 2013. www.nice.org.uk
- Practice Committees of the ASRM and SREI. Optimizing natural fertility: a committee opinion. Fertility and Sterility 2022;117(1):53-63. doi:10.1016/j.fertnstert.2021.10.007. integration.asrm.org
- American College of Obstetricians and Gynecologists (ACOG). Evaluating Infertility. acog.org. 2020 (revisado 2026). www.acog.org
- NHS. Planning your pregnancy. nhs.uk. 2026. www.nhs.uk
- Organización Mundial de la Salud (OMS). 1 in 6 people globally affected by infertility. who.int. 2023. www.who.int
This guide is for educational purposes and does not replace assessment by a health professional. If you have concerns about your fertility, a health condition or regular medication, or you have been trying for a while, seek advice.